Skip to content
Prof. Dr. Ali Avanoğlu
Main treatment page • Hypospadias Surgery

Hypospadias Surgery in Turkey

Hypospadias is a congenital difference in which the urinary opening forms lower on the underside of the penis instead of at the tip. Treatment is not a single named operation — the technique and the number of stages depend on where the opening is, how much curvature is present, and the condition of the tissue.

ByProf. Dr. Ali AvanoğluUpdated
At a glance 47 pages • 19 video
6–18 months
Treatment age

The most commonly preferred window for repair

One or two stages
Number of operations

Determined by the opening's location and the tissue available

Two specialists
Surgical team

Decisions are made together, in the operating room

The whole treatment • 14 sections

This page explains the whole picture; the details of each topic are in the pages below

Start with what hypospadias is, then move through the questions families and adult patients ask most: from recognizing it, to how the surgical plan is chosen, to what adult presentation looks like.

hypospadias
01Section 1 / 14

What is hypospadias?

Hypospadias is usually noticed at the very first examination

Hypospadias is a congenital difference in which the urinary opening (meatus) forms not at the tip of the penis but further back, on its underside. It is one of the most common congenital penile differences in baby boys, and it is usually noticed at the very first examination after birth.

Definitionthree components
  • 1The urinary opening sits backnot at the tip of the penis, but on the underside — anywhere from just below the tip to the scrotum
  • 2A hooded foreskingathered on top, incomplete underneath
  • 3Downward curvatureduring erection; not present in every case
Quick factsat a glance
WhenCongenital; usually noticed at the first examination
TreatmentDoes not improve with medication or time; surgical repair
AgeUsually 6–18 months
SurgeryOne stage, or a planned two stages
CircumcisionNot done before repair; the skin is preserved
Popularly described as a 'born circumcised' look

This is not a form of circumcision — it is a congenital difference in which the urinary opening forms further back than it should.

Read the full text
  • The opening can sit just below the tip, at the base of the penis, or on the scrotum. Where it opens determines the type of hypospadias — and the type determines how the surgery is planned.
  • In most cases, two further findings accompany the picture: the foreskin gathers like a hood on top and stays incomplete underneath, and the penis curves downward during erection. In some children, an undescended testicle is also present.
  • Hypospadias does not improve with medication or with time. Treatment is surgical, usually performed between 6 and 18 months of age, in one or two stages depending on the opening's location and the condition of the tissue. Early diagnosis matters: in a baby where hypospadias is suspected, circumcision is postponed so the skin that will be needed for the repair is preserved.
Videos in this sectionFull guide (19) →
born circumcised baby
02Section 2 / 14

The congenital appearance often described as 'born circumcised'

A congenital 'born circumcised' look is not a diagnosis on its own

Families usually hear the word hypospadias for the first time at the examination; what is noticed at home is usually that the baby looks as if he was “born circumcised.” This appearance is the foreskin gathering like a hood on top while staying incomplete underneath.

  • The appearance on its own is not a diagnosis. In most babies it means the urinary opening forms further back than it should — that is hypospadias. In some babies, though, the opening is exactly where it should be. Examination is what tells the two apart.
  • Because of this, circumcision should never be planned for a baby with this appearance before the position of the urinary opening has been directly seen. The foreskin is the single most valuable spare tissue for the repair, if it turns out to be needed.
Videos in this sectionFull guide (19) →
The general logic behind hypospadias treatment
03Section 3 / 14

The general logic behind hypospadias treatment

The repair's three goals are the same in every case

Hypospadias repair has three goals, and they hold in every case: move the urinary opening to the tip of the penis, straighten the penis, and achieve a natural appearance.

Three goalsthe same in every case
  • 1Moving the opening to the tipthe urinary channel is completed all the way to the tip of the penis
  • 2Straightening the peniscurvature is measured and corrected
  • 3A natural appearancea well-formed head, circumcised or with foreskin
What determines the routethree findings
FindingWhat it changes
The opening's locationthe further from the tip, the longer the channel to be built
Curvaturecurvature beyond 30° changes the plan
The urethral plateif healthy, one session; if not, the process is split in two
Read the full text
  • What changes from child to child is not the goal but the route taken to reach it.
  • Three findings determine that route. First, the position of the opening: the further back it is, the longer the new channel that has to be reconstructed.
  • Second, curvature: a curve beyond roughly 30 degrees changes the plan.
  • Third, the urethral plate — the tissue bed the new channel is built on. If it is healthy, one operation is usually enough; if not, the repair is split into two stages.
  • All three of these findings are only confirmed on the operating table, after the skin has been opened and an artificial erection test performed. That is why a sound hypospadias plan is never a single scenario — it is prepared for both possible outcomes.
Much of the decision is made on the operating table

The location of the opening is visible on examination, but the true degree of curvature and the quality of the urethral plate only become clear once the skin has been opened. A good plan is therefore never built around a single scenario — it is prepared for two, and both possibilities should be discussed during consent.

Videos in this sectionFull guide (19) →
what is hypospadias
04Section 4 / 14

How is it recognized? Signs and diagnosis of hypospadias

Four signs: the opening's position, the foreskin, the stream, curvature

Hypospadias is usually noticed right after birth, at the first examination. There are four things families can watch for at home.

What to watch for at homefour signs
  • 1The urinary opening's positionnot at the tip, but further back on the underside
  • 2The foreskin's shapegathered like a hood on top, incomplete underneath
  • 3The urine streampoints downward, sprays, or doesn't come out in one direction
  • 4Curvature during erectiona downward curve
Not every child has all of them

In children whose opening is very close to the tip, a slightly downward stream may be the only sign; the foreskin can look normal while the opening is still set back.

Read the full text
  • First, the position of the urinary opening: not at the tip, but set further back on the underside. Second, the distribution of the foreskin: gathered like a hood on top, incomplete underneath.
  • Third, the urine stream: it points downward, sprays, or does not come out in a single direction. Fourth, downward curvature seen during erection.
  • Not every child has all of these findings. In some children whose opening is very close to the tip, a slightly downward stream may be the only sign.
  • One exception is worth knowing on its own: the foreskin can look completely normal while the opening is still set back. This subtype is usually only discovered during circumcision itself.
  • That is why, in every baby scheduled for circumcision, the underside of the penis should be examined in good light before the procedure.
The underside should always be checked before circumcision

The foreskin can look entirely normal while the opening is still set back — this subtype is often only discovered during circumcision itself, by which point the most valuable spare tissue has already been removed. In every baby scheduled for circumcision, the underside of the penis should be examined in good light beforehand.

Videos in this sectionFull guide (19) →
Why does hypospadias happen?
05Section 5 / 14

Why does hypospadias happen?

In the first three months of pregnancy the channel closes toward the tip

Hypospadias arises when the final stage of the urinary channel's formation does not complete while the baby is still in the womb. In the first three months of pregnancy, the channel closes from the underside of the penis toward the tip, like a zipper; if this closing stops early, the opening stays where it stopped. How far back the opening is shows where the closing stopped.

Contributing factorstogether
  • 1Genetic predispositionmore common in babies whose father or brother has hypospadias
  • 2Hormonal influencesduring the first three months of pregnancy
  • 3Environmental factorsrelated to the pregnancy period
Nothing was done wrong

It is not the result of anything done or not done during pregnancy; there is no behaviour a parent can be held responsible for.

It does not resolve on its own

It is a structural difference; not every case needs surgery, however — in some children with a very tip-close opening, a straight stream, and no curvature, watchful follow-up can be discussed.

Read the full text
  • There is no single cause. Genetic predisposition, hormonal influences, and environmental factors during pregnancy are all thought to play a part together. A family history of hypospadias raises the likelihood; babies whose father or brother has hypospadias have a higher-than-average chance of it too.
  • Families most often carry two questions: was something done wrong, and will it happen again? The answer to the first is clear — it is not the result of anything done or not done during pregnancy; there is no behaviour a parent can be held responsible for. For the second, genetic counselling can help, but in most families it occurs in only one child.
  • One point is worth underlining: hypospadias is a structural difference and does not resolve on its own with time. That said, not every case needs surgery — in some children with a very tip-close opening, a straight stream, and no curvature, watchful follow-up can also be discussed.
Videos in this sectionFull guide (19) →
hypospadias surgery
06Section 6 / 14

Surgical paths for hypospadias in children

Repair age in children is usually 6–18 months

In children whose opening is close to the tip — the distal group — repair is completed in a single operation.

By the opening's locationthree paths
GroupWhere's the opening?RepairStay
Distalclose to the tipone operation, no planned second stagesame day / next day
Midshaftmiddle of the shaftone session if there's no curvature and the plate is usable; a narrow plate with a small graftusually 1 night
Proximalbase, scrotum, or further backcurvature is common; a significant share get a planned two-stage repair1–2 nights
When curvature and an inadequate plate combine

The two problems compound each other; planning is done with the greatest care (complex repair).

Read the full text
  • This group makes up most cases. The child usually goes home the same day or the next day, and there is no planned second stage.
  • When the opening is in the middle of the shaft, the decision is not made by a single rule. If there is no curvature and the plate is usable, a single session is still the goal; if the plate is narrow, it can be widened with a small graft and completed in the same operation.
  • When the opening is at the base, on the scrotum, or further back still, the picture changes. Curvature accompanies this group often, and correcting it leaves an opening on the underside.
  • Tissue added there cannot be made into a tube until it has established its own blood supply. That is why, in a significant share of proximal cases, the repair is deliberately split into two stages.
  • Cases where curvature is pronounced and the plate is also inadequate are a separate category; here two problems compound each other, and planning is done with the greatest care.
Videos in this sectionFull guide (19) →
One operation, or two stages?
07Section 7 / 14

One operation, or two stages?

A planned two-stage repair is a predictable path

This is the question families find hardest, and the answer rests on necessity, not preference.

The decisionnot a preference, a necessity
One stageplate healthy, curvature mild
  • The groove is preserved and deepened
  • The channel is built in the same session
  • Distal and most midshaft cases
Two stageswhen curvature correction leaves an opening
  • Stage 1: straightening + foundation (tissue is added)
  • ≈ 6 months to mature; the child continues normal life
  • Stage 2: the channel is built
Two stages is not a failure

When a repair forced into a single session breaks down, three or four corrective procedures can follow; a planned two-stage repair is a predictable path.

Read the full text
  • When curvature is corrected, new tissue is added in place of the unhealthy tissue that was removed. If that tissue is made into a channel right away, it contracts and results in a narrowing.
  • That is why the foundation is prepared in one session, roughly six months are allowed for it to mature, and the channel is built in a second session.
  • Two stages is a choice that reduces the number of operations rather than adding to them. When a repair is forced into a single session and it breaks down, three or four corrective procedures can follow; a planned two-stage repair is a predictable path instead.
  • During the interval, the child continues normal life: bathing, going to nursery, playing. Urine passes through the wide opening on the shaft, and this period is temporary.
Two stages is not a failure

A staged repair is not a second operation performed because of a complication — it is two steps planned from the start. When a repair is forced into a single session and it breaks down, three or four corrective procedures can follow; a planned two-stage repair is a predictable path instead. In other words, it is the choice that reduces the total number of operations, not one that adds to it.

Videos in this sectionFull guide (19) →
Prof. Dr. Ali Avanoğlu's publications on this topic · 1
  1. Tiryaki S, Ələkbərova V, Dokumcu Z, et al. (2016). Unexpected outcome of a modification of Bracka repair for proximal hypospadias: High incidence of diverticula with flaps. Journal of pediatric urology. PubMed ↗
how is penile curvature corrected
08Section 8 / 14

Techniques used in hypospadias surgery

The technique is chosen by the condition of the plate and tissue

The most commonly used method is deepening the existing groove along the midline and turning it into a tube (the TIP/Snodgrass technique). Because the channel is built from the patient's own tissue, no extra tissue needs to be harvested, and the opening looks natural.

Techniqueswhen they're used
MethodWhat's doneWhen
TIP (Snodgrass)The groove is deepened along the midline and turned into a tubemost common; when the plate can be used
Graft-supported repairA narrow plate is widened with a small graftwhen the plate is narrow
Oral mucosaA thin layer taken from inside the cheekwhen there's no plate / a repeat repair
Curvature correctionShortening the top surface or lengthening the undersidebased on the angle and priority
Interposition layerLiving tissue placed over the channelin every technique — prevents fistula
Read the full text
  • When the plate is narrow, this method is supported with a small graft.
  • When the plate cannot be used at all, or when a repeat repair is involved, oral mucosa comes into play. This thin layer taken from inside the cheek is the most reliable spare tissue in this surgery, because it tolerates a moist environment well and contains no hair.
  • There are two routes for correcting curvature: shortening the top surface or lengthening the underside. The first is simpler and brings some shortening in length; the second preserves length but is more extensive. The choice is made based on the angle and the patient's priorities.
  • One detail is common to every technique: a layer of living tissue laid over the new channel. This layer is the main technical safeguard against fistula, the most common problem after this surgery.
Videos in this sectionFull guide (19) →
Doç. Dr. Yaşar Issı's publications on this topic · 1
  1. Issi Y, Bilir C (2022). Dorsal Dartos Flap Prepared Before Urethroplasty, Less Bleeding of Operation: A New Perspective on Hypospadias. Turkish journal of urology. PubMed ↗
hypospadias surgery reviews
09Section 9 / 14

Hypospadias surgery: the process and recovery

Catheter and dressing during recovery

The operation is performed under general anaesthesia and takes between 1 and 4 hours depending on its scope. Distal repairs usually need only a day-case stay or a single night; proximal and staged repairs can mean a stay of one or two nights.

The processhow long it takes
AnaesthesiaGeneral anaesthesia
Duration1–4 hours depending on scope
StayDistal: day-case / 1 night · Proximal and staged: 1–2 nights
Catheter5–14 days; drains into the nappy in babies; painless to remove
DressingPressure dressing if a graft was used; must not be disturbed in the first days
Swelling / bruisingSettles in 2–4 weeks
Final appearanceTakes shape over months; don't judge the result from the early look
Read the full text
  • A thin catheter stays in place for 5 to 14 days depending on the scope of the repair, and in babies it is left to drain into the nappy. Removing it is painless.
  • If a graft was used, keeping the pressure dressing over it undisturbed in the first few days is the single most critical detail for the graft to take.
  • Swelling and bruising are expected findings and settle within two to four weeks. The final appearance takes shape over months — it's important not to judge the result from how things look in the early period.
Videos in this sectionFull guide (19) →
What happens in the operating room? Step by step
10Section 10 / 14

What happens in the operating room? Step by step

Every step through the two specialists' shared assessment

The repair always proceeds in the same order; what changes is how much each step involves. Knowing the sequence makes it easier to follow what your surgeon describes.

Step by stepalways the same order
  1. 1Marking the boundariesthe opening and surrounding tissue are marked
  2. 2Skin release + measurementpart of the tension-related curvature resolves; the angle is measured with an artificial erection
  3. 3Clearing the band + re-measuringunhealthy connective tissue is cleared for any remaining curvature; the opening can shift back
  4. 4Foundation and channelthe groove is preserved or tissue is added; the channel is built, a protective layer is laid, the head is closed, the skin is arranged
  5. 5Catheter and dressinga pressure dressing if a graft was used; must not be disturbed in the first days
Read the full text
  • The first step is marking the boundaries of the opening and the surrounding tissue. Next, the penile skin is released down to the base — on its own, this removes part of the curvature caused by skin tightness. Then a measurement is taken: an erection is created with saline, and the remaining angle is seen.
  • If curvature remains, the unhealthy connective tissue beneath the channel is cleared and the measurement is repeated. At this step the opening can shift further back — a case that looked distal can turn out to belong to a more posterior group. This is expected, and it is why the plan is kept flexible.
  • Next comes the foundation. If the groove is healthy, it is preserved and, if needed, deepened and widened along the midline; if it is inadequate, it is removed and tissue is added in its place. The channel is built on this foundation, a protective tissue layer is laid over it, the head of the penis is closed over the channel, and the skin is arranged.
  • In the final step, a thin catheter is placed and a dressing applied. If a graft was used, the dressing is a pressure dressing and is expected to stay undisturbed in the first few days; the graft taking depends on it.
Videos in this sectionFull guide (19) →
hypospadias surgery reviews
11Section 11 / 14

Situations that can follow hypospadias surgery

Problems are caught early when they're recognized

Hypospadias surgery is the work of building a new piece of an organ out of the body's own tissue; because of that, it is possible to encounter certain situations during recovery. Knowing about them in advance also means knowing what to do if they appear.

What to know aboutpossible situations
  • 1Fistulaa small opening between the channel and the skin that leaks urine — the most common
  • 2Narrowing of the opening / channelthe stream thins; checked for before closing
  • 3Sutures opening at the tipthe opening shifts back
  • 4Pouch formation (diverticulum)ballooning while urinating
  • 5Return of curvatureespecially during adolescence
  • 6Appearancecosmetic assessment
Read the full text
  • The most common situation is a small opening forming between the repaired channel and the skin, through which urine leaks. The most critical point in repairing it is not missing a narrowing further along the channel before closing it — this is the leading cause of repeat repairs.
  • Narrowing of the opening or the channel, sutures opening at the head of the penis, part of the channel ballooning into a pouch, and the return of curvature are the other main topics. Each has its own way of being assessed and repaired.
  • The factor that most determines how likely these situations are is the surgeon's experience with this operation and the accuracy of the decisions made on the table.
Any narrowing further along the channel should be ruled out before a fistula is closed

If there is an obstruction in the channel, urine keeps finding its way out through the fistula instead of the path offering resistance, and the closure fails. This is the most common reason repeat fistula repairs are needed. Ask your doctor this question directly, and how it is checked.

Videos in this sectionFull guide (19) →
Prof. Dr. Ali Avanoğlu's publications on this topic · 2
  1. Yagmur I, Tekin A, Bağcı U, et al. (2022). Acquired Penile Epidermoid Cysts in Children. Cureus. PubMed ↗
  2. Ulman I, Erikçi V, Avanoğlu A, et al. (1997). The effect of suturing technique and material on complication rate following hypospadias repair. European journal of pediatric surgery. PubMed ↗
Recurrent hypospadias (redo) and complex cases
12Section 12 / 14

Recurrent hypospadias (redo) and complex cases

The tissue that's left determines the technique

In a patient who has had more than one operation, the question is no longer “which technique” but “what tissue do we have left.”

Two common mistakesin recurrent cases
  • 1Rushinga procedure done before the scar has softened fails again
  • 2Addressing problems one at a timenarrowing, fistula and curvature need to be mapped together
If there's skin disease (BXO)

White, hardened tissue around the opening: skin grafts aren't used, oral mucosa is preferred, and the process is staged.

The permanent-opening option

In some cases, instead of rebuilding the whole channel, a permanent opening that allows predictable urination can be chosen — a deliberate choice.

Read the full text
  • Every procedure reduces the tissue available and the blood supply to that area. That is why a third repair cannot be planned with the same logic as the first.
  • Two mistakes are common in this group: rushing, and addressing problems one at a time. Procedures performed before scar tissue has softened tend to fail again; narrowing, fistula and curvature more often than not feed into one another, and repairs made without mapping all of them together rarely last.
  • An overlooked cause of recurrent narrowing is skin disease. If there is white, hardened tissue around the opening, the plan changes from the outset: skin grafts are not used, oral mucosa is preferred instead, and the process is carried out in stages.
  • In some cases, rather than rebuilding the entire channel, a permanent opening that allows trouble-free, predictable urination can be chosen instead. This is not giving up — it is a deliberate choice.
Videos in this sectionFull guide (19) →
hypospadias surgery in adults
13Section 13 / 14

Hypospadias in adults

In adults, the patient's complaint sets the goal

The most important difference in adult decision-making, compared with children, is this: the goal is set by the patient's complaint, not by anatomy alone.

Complaint → planthe patient sets the goal
Leading complaintPlan
Can't urinate standing / spraying streamcompleting the opening and channel
Curvature making intercourse difficultcurvature correction
Appearancea cosmetically-focused repair
Ejaculation problemscompleting the channel to the tip
Two groupsin adulthood
  • 1Never operated onthe plan follows the complaint
  • 2Repaired in childhoodmost often a channel narrowing; appears during adolescent growth; hair-bearing skin repairs bring hair, stones, infection
Not a cause of infertility

The problem is usually not in production but in the delivery of semen; it can improve with repair.

Read the full text
  • Difficulty urinating while standing, a spraying stream, curvature that makes intercourse difficult, dissatisfaction with appearance, or issues with ejaculation — whichever of these is the leading concern shapes the plan.
  • Some adult patients were never operated on as children; others were repaired in childhood and develop a problem years later. In this second group, the most common issue is a narrowing of the channel, which often appears during adolescent growth.
  • In cases repaired in childhood using hair-bearing skin, hair can grow inside the channel after puberty, leading to stone formation, odour and recurrent infection. The lasting solution is replacing that segment with hair-free tissue.
  • Concern about fertility comes up often in this group. Hypospadias alone is not a cause of infertility; the issue is usually one of delivery rather than production, and it can improve with repair.
Hypospadias alone is not a cause of infertility

The problem is usually not sperm production but sperm delivery: when the opening is set back, semen cannot be projected forward with enough force. This is a mechanical problem, and it usually resolves once the channel is completed to the tip. Clarity comes from semen analysis and hormone testing, not from guesswork.

Videos in this sectionFull guide (19) →
Hypospadias follow-up: the file doesn't close with surgery
14Section 14 / 14

Hypospadias follow-up: the file doesn't close with surgery

The file doesn't close with surgery

Hypospadias is not a file that closes with surgery. Some problems appear years later, as the penis grows; that is why follow-up extends from infancy into adulthood.

Timelineinfancy to adulthood
InfancyRepair and early check-ups
ChildhoodMonitoring the stream and appearance
AdolescenceThe most critical period: a hidden length difference becomes visible as curvature; narrowing if the channel can't keep pace with growth; hair growth if hair-bearing tissue was used
AdulthoodA single assessment even without complaints; uninterrupted follow-up with the same team
Read the full text
  • Adolescence is the most critical period. A length difference not noticed at a young age becomes visible as curvature during this time.
  • If the repaired channel cannot keep pace with growth, a narrowing appears; if the tissue used carries hair, hair growth begins.
  • Even without complaints, a single assessment during this period can prevent far more extensive procedures later.
  • Follow-up continuing without interruption from childhood into adulthood is what allows late problems to be caught early.
Videos in this sectionFull guide (19) →
Roadmap • Interactive tool

Assess your situation yourself

Answer a few questions; the anatomical diagram updates as you go. At the end you're guided to the section and pages that fit your situation, and you can send the summary to the doctor by WhatsApp. About 2 minutes; your answers stay on your device.

Hypospadias RoadmapStep-by-step assessment
Step 1
Loading tool…
Hypospadias Surgery video guide • 19 video

What people ask about Hypospadias Surgery, in short videos

Prepared in order for those new to the topic: first what hypospadias is and why it occurs, then the surgical decision and preparation, and finally after-surgery care and the long term.

Viewing order1–4 / 19
Frequently asked questions

The first 8 questions families ask

Short answers to the questions families ask most often.

Ask your question on WhatsApp
Does hypospadias correct itself over time?
No. It is a structural difference and does not resolve on its own. Not every case needs surgery, however — in some children with a very tip-close opening and an unaffected stream, watchful monitoring can also be discussed.
What is the best age for surgery?
Generally 6 to 18 months is preferred. Tissue healing is favourable at this age, the child will not remember the procedure, and it falls before toilet training. Surgery is also performed outside this window — only the preparation and expectations change.
How many operations will be needed?
Most distal cases need only one operation. In proximal cases, and when curvature is pronounced, the process is often split into two stages. The final decision is made once the plate and the curvature have been assessed during surgery.
Can circumcision be done beforehand?
No. The foreskin is the single most valuable spare tissue for the repair, if it is needed. Circumcision is completed in the same session as the hypospadias repair.
Are sexual function and having children affected after surgery?
Hypospadias alone is not a cause of infertility. Issues with ejaculation are usually mechanical and improve once the channel is completed to the tip. Any other accompanying conditions are assessed separately.
Is hypospadias hereditary — will it happen in a future child?
A family history raises the likelihood, but in most families it occurs in only one child. Rather than giving a fixed recurrence rate, genetic counselling is the more accurate route if you are planning another pregnancy.
Did we do something wrong during pregnancy?
No. Hypospadias is not the result of anything a parent did or did not do during pregnancy. It arises when the final stage of normal development does not fully complete.
Who performs the surgery?
The repair is carried out together by two pediatric urology specialists. Prof. Dr. Ali Avanoğlu is also a pediatric surgeon; Doç. Dr. Yaşar Issı is additionally trained in adult urology.
Our surgeons · two specialists, one team

One operation, two surgeons

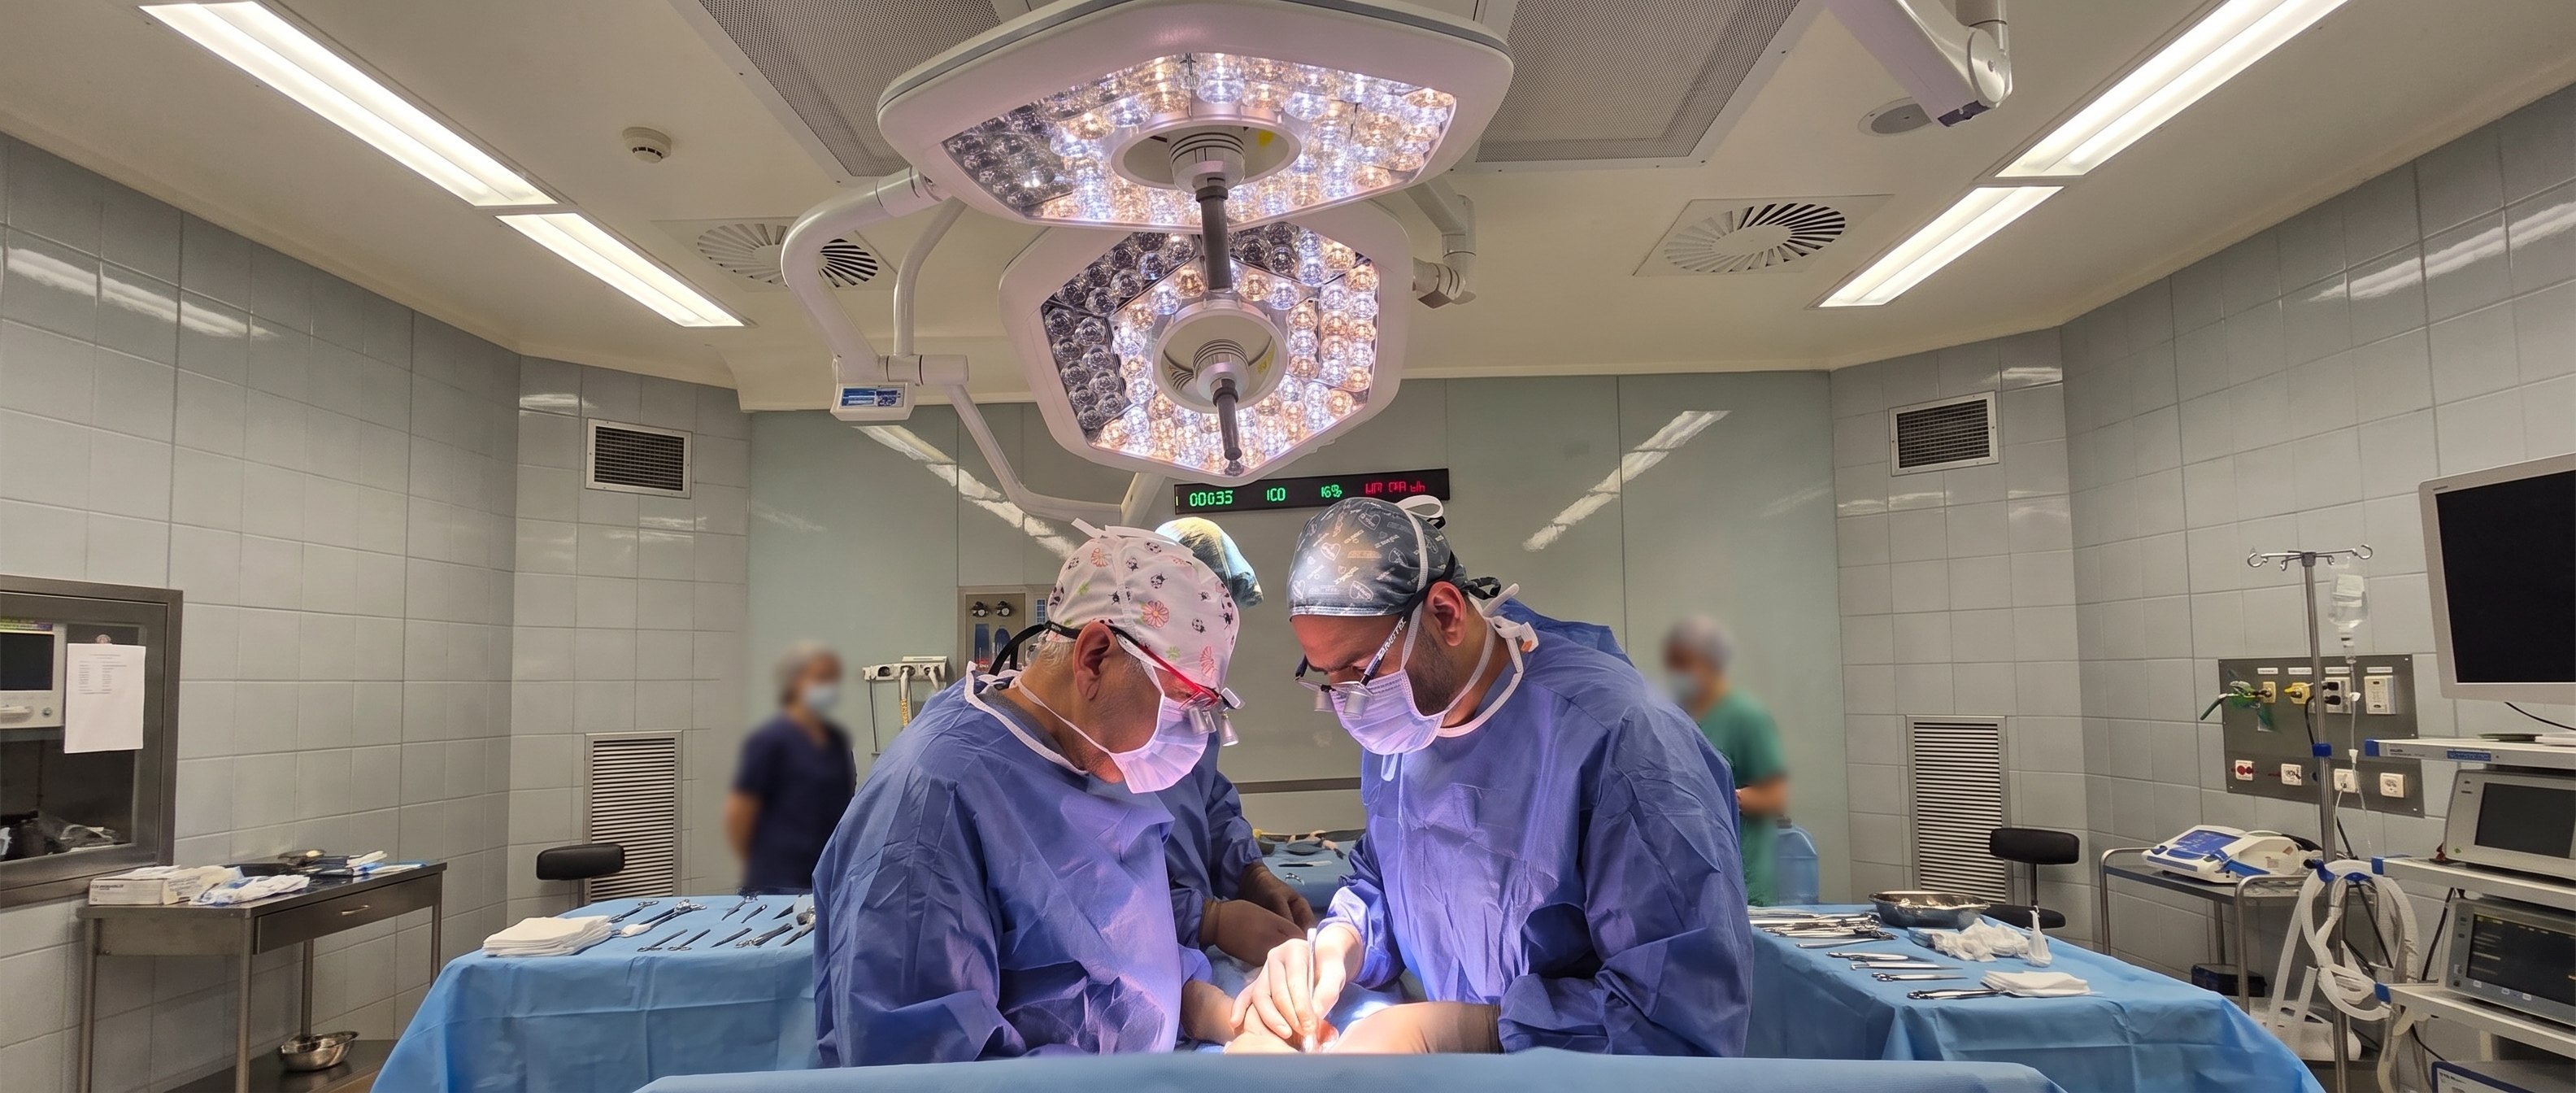
Two pediatric urology specialists work together on every operation: one performs the repair while the other assists, checks, and takes over when needed. This built-in second opinion completes demanding operations with less risk.

  • Lower risk

    A shared assessment and four-handed technique; a second experienced pair of eyes at the demanding steps.

  • Shorter surgery

    Working in parallel shortens the time spent under anesthesia.

  • Less anesthesia

    Infants and young children spend less time under anesthesia.

Prof. Dr. Ali Avanoğlu — hypospadias surgeon, Turkey

Prof. Dr. Ali Avanoğlu

Pediatric Surgeon and Pediatric Urologist

Over forty years in medicine, thirty-two of them as a pediatric surgeon; focused exclusively on pediatric urology since 1994. Associate professor in 1996 and full professor in 2002 at Ege University, where he chaired both the Department of Pediatric Surgery and the Division of Pediatric Urology. Roughly 3,000 hypospadias repairs and more than 1,000 operations for vesicoureteral reflux.

Doç. Dr. Yaşar Issı — hypospadias surgeon, Turkey

Doç. Dr. Yaşar Issı

Pediatric and Adult Urologist

Graduate of Ege University Faculty of Medicine (2006); completed urology training at İzmir Atatürk Training and Research Hospital (2011) and a pediatric urology fellowship at Ondokuz May University (2016); associate professor since 2022. Has worked at Gaziantep Children's Hospital, İzmir Çiğli Training and Research Hospital, and Bakırçay University. More than 1,000 hypospadias repairs and a comparable number of stone operations; continues the same patients' follow-up from childhood through adolescence and adulthood, in the same team.

Why together?

What operating together means for your child

In every operation, it is not a surgeon and an assisting resident — it is two specialists who both know the procedure, working together. We summarize the difference in four points.

Difference 01

Critical decisions are made together

Which technique to use, whether the repair will finish in one session, and how to respond to anything unexpected during surgery are decided by two specialists' shared assessment — never by one person alone.

Shared decision
Two pediatric urology surgeons
Together, in the same team, every time
Two hypospadias surgeons operating together
Difference 02

Shorter time under anesthesia

While one surgeon finishes a step, the other prepares the next; four hands work at once. In an infant or young child, every extra minute under anesthesia is a risk in its own right.

Two hands, at the same time
Difference 03 Related conditions, same session
1×

One anesthesia: conditions found together (undescended testis, inguinal hernia, hydrocele, hydronephrosis) are planned into the same session.

Get in touch
Difference 04 — Follow-up never breaks off

Some issues only surface during adolescence or adulthood. Because the team includes both pediatric and adult urology, follow-up never breaks off between childhood and adulthood.

Pediatric urology
Adult urology
Same team, same record
Process · for patients travelling from abroad too

Travelling to Turkey for treatment?

Surgery takes place at İzmir Acıbadem Kent Hospital; our clinic is about 4–5 km from the hospital, with a range of accommodation options nearby. The process runs in coordination between the clinic and the hospital, from your first consultation through to the completion of post-operative checks.

Clinic Hospital İzmir Acıbadem Kent Hospital · about 4–5 km.
  1. 01 Clinic
    Pre-treatment review with two pediatric urology surgeons — family on a video call from home

    Consultation and surgical planning

    Patients are first assessed at our clinic; surgical planning is done here.

    Avanoğlu–Issı Clinic

  2. 02 Hospital
    Prof. Dr. Ali Avanoğlu and Doç. Dr. Yaşar Issı, hypospadias surgeons in İzmir, Turkey

    Pre-operative tests and anesthesia review

    One day before surgery, you are referred to İzmir Acıbadem Kent Hospital for the required tests and anesthesia assessment.

    One day before surgery

  3. 03 Hospital
    Two pediatric urology surgeons' treatment process — family arriving at the hospital

    Surgery

    The operation takes place the next day, as planned. In suitable cases, it is completed as day surgery.

    İzmir Acıbadem Kent Hospital

  4. 04 Clinic
    Two pediatric urology surgeons' treatment process — remote follow-up after surgery, mother on a video call from home

    Recovery after discharge

    After the observation period, patients who meet discharge criteria continue recovering at home or at their accommodation. Dressing changes, wound checks, and catheter checks and removal continue at our clinic.

    Avanoğlu–Issı Clinic

Frequently asked by families

What families travelling from abroad ask first

Short answers are below; write to us directly with any question about your trip.

Let's plan your trip together
  • İzmir, Turkey
  • Two pediatric urology specialists
  • Same team from diagnosis to follow-up
Where do the operations take place?
Surgery takes place at İzmir Acıbadem Kent Hospital. Our clinic is about 4–5 km from the hospital, with a range of accommodation options nearby.
How does the process work, from consultation to surgery?
You are first assessed at our clinic, where the surgical plan is made. One day before surgery you are referred to the hospital for the required tests and anesthesia review; the operation itself takes place the following day, as planned.
Do we stay in hospital after surgery?
A significant share of our operations, when suitable, are completed as day surgery. Patients who meet discharge criteria continue recovering, after the observation period, in the more comfortable setting of your home or accommodation.
How are post-discharge checks handled?
Follow-up steps such as dressing changes, wound checks, and catheter checks and removal continue to take place at our clinic. That way, the entire process — from the first consultation through to the completion of follow-up — runs in coordination between the clinic and the hospital.
Topic index • 7 clusters

All hypospadias topics

7 clusters, 47 detail pages. Each page focuses on a single question and links back here, to the main treatment page.

Recurrent Cases4

Surgery for complex cases that have already had more than one operation.

Scientific publications · 14 articles

Prof. Dr. Ali Avanoğlu and Doç. Dr. Yaşar Issı's publications on Hypospadias Surgery

Articles indexed in PubMed; the complete set of citations from the pages above. For all publications, see the Publications page →

  1. Tiryaki S, Issi Y (2023). The association of meatal stenosis and infant circumcision. The Turkish journal of pediatrics. PubMed ↗
  2. Yagmur I, Tekin A, Bağcı U, et al. (2022). Acquired Penile Epidermoid Cysts in Children. Cureus. PubMed ↗
  3. Issi Y, Bilir C (2022). Dorsal Dartos Flap Prepared Before Urethroplasty, Less Bleeding of Operation: A New Perspective on Hypospadias. Turkish journal of urology. PubMed ↗
  4. Şentürk Pilan B, Özbaran B, Çelik D, et al. (2021). Quality of Life and Psychological Well-being in Children and Adolescents with Disorders of Sex Development. Journal of clinical research in pediatric endocrinology. PubMed ↗
  5. Şentürk Pilan B, Özbaran B, Çelik D, et al. (2020). Psychiatric view for disorders of sex development: a 12-year experience of a multidisciplinary team in a university hospital. Journal of pediatric endocrinology & metabolism. PubMed ↗
  6. Tiryaki S, Tekin A, Yagmur İ, et al. (2018). Parental Perception of Terminology of Disorders of Sex Development in Western Turkey. Journal of clinical research in pediatric endocrinology. PubMed ↗
  7. Tiryaki S, Ələkbərova V, Dokumcu Z, et al. (2016). Unexpected outcome of a modification of Bracka repair for proximal hypospadias: High incidence of diverticula with flaps. Journal of pediatric urology. PubMed ↗
  8. Özbaran B, Özen S, Gökşen D, et al. (2013). Psychiatric approaches for disorders of sex development: experience of a multidisciplinary team. Journal of clinical research in pediatric endocrinology. PubMed ↗
  9. Kavakli K, Avanoglu A, Celik A (2005). Cost-effectivity of circumcision in hemophilia. Journal of pediatric surgery. PubMed ↗
  10. Celik A, Ulman I, Ozcan C, et al. (2003). Reconstruction of penile shaft amputation: is microvascular re-anastomosis mandatory? BJU international. PubMed ↗
  11. Kavakli K, Nisli G, Ozcan C, et al. (1997). Safer and much cheaper circumcision using fibrin glue in severe haemophilia. Haemophilia. PubMed ↗
  12. Ulman I, Erikçi V, Avanoğlu A, et al. (1997). The effect of suturing technique and material on complication rate following hypospadias repair. European journal of pediatric surgery. PubMed ↗
  13. Avanoğlu A, Ulman I, Herek O, et al. (1996). Posterior urethral injuries in children. British journal of urology. PubMed ↗
  14. Ulman I, Avanoğlu A, Gökdemir A (1995). Neuroanatomy of the human striated urethral sphincter. British journal of urology. PubMed ↗
Contact us

With the hypospadias assessment that fits your situation would you like to reach the doctor?

There are two ways. If you'd like the doctor to already know your situation before replying, start with the short assessment; if your question is brief, write to us directly. Both reach the same team.

1 Let me assess my situation firstRecommended The Roadmap asks a few questions in about 2 minutes, collects your answers with an anatomical diagram, and produces a ready-made summary. That summary is added to your WhatsApp message — the doctor replies already knowing your situation. Start the Roadmap
2 I'll write directly Fill in the form; your message opens ready-made in WhatsApp (you can edit it before sending), or you can send it directly by email. This page's topic is added to the message automatically.

Editor's note: Age and a short sentence are enough; you don't need to use medical terms. Please don't send photos — the doctor will request them through a secure channel if needed. What you write is only sent when you submit it; this page does not store anything.

Direct contactReply comes from the doctor
Who is this for?
Quick questions:

Your message is not stored on our server; it is sent by WhatsApp/email. Privacy notice →

Gomauna Web Design and Development gomauna.com Prof. Dr. Ali Avanoğlu | 2026 © All Rights Reserved. SEO & GEO OPTIMIZED
WhatsApp Roadmap